GI Endoscopy · 8 min read
Barrett Surveillance in 2026: Prague C&M, Seattle Protocol, and When to Eradicate
Diagnose at least 1 cm of salmon mucosa with intestinal metaplasia. Report Prague C&M. HD chromo plus Seattle. Resect visible lesions before you ablate.
Barrett esophagus is salmon mucosa at least 1 cm above the top of the gastric folds plus intestinal metaplasia. Report Prague C and M. Inspect with HD white light and chromoendoscopy, target visible lesions, then take Seattle biopsies. Resect lumps before you ablate. Confirmed high-grade dysplasia or T1a goes to endoscopic eradication, not routine esophagectomy.
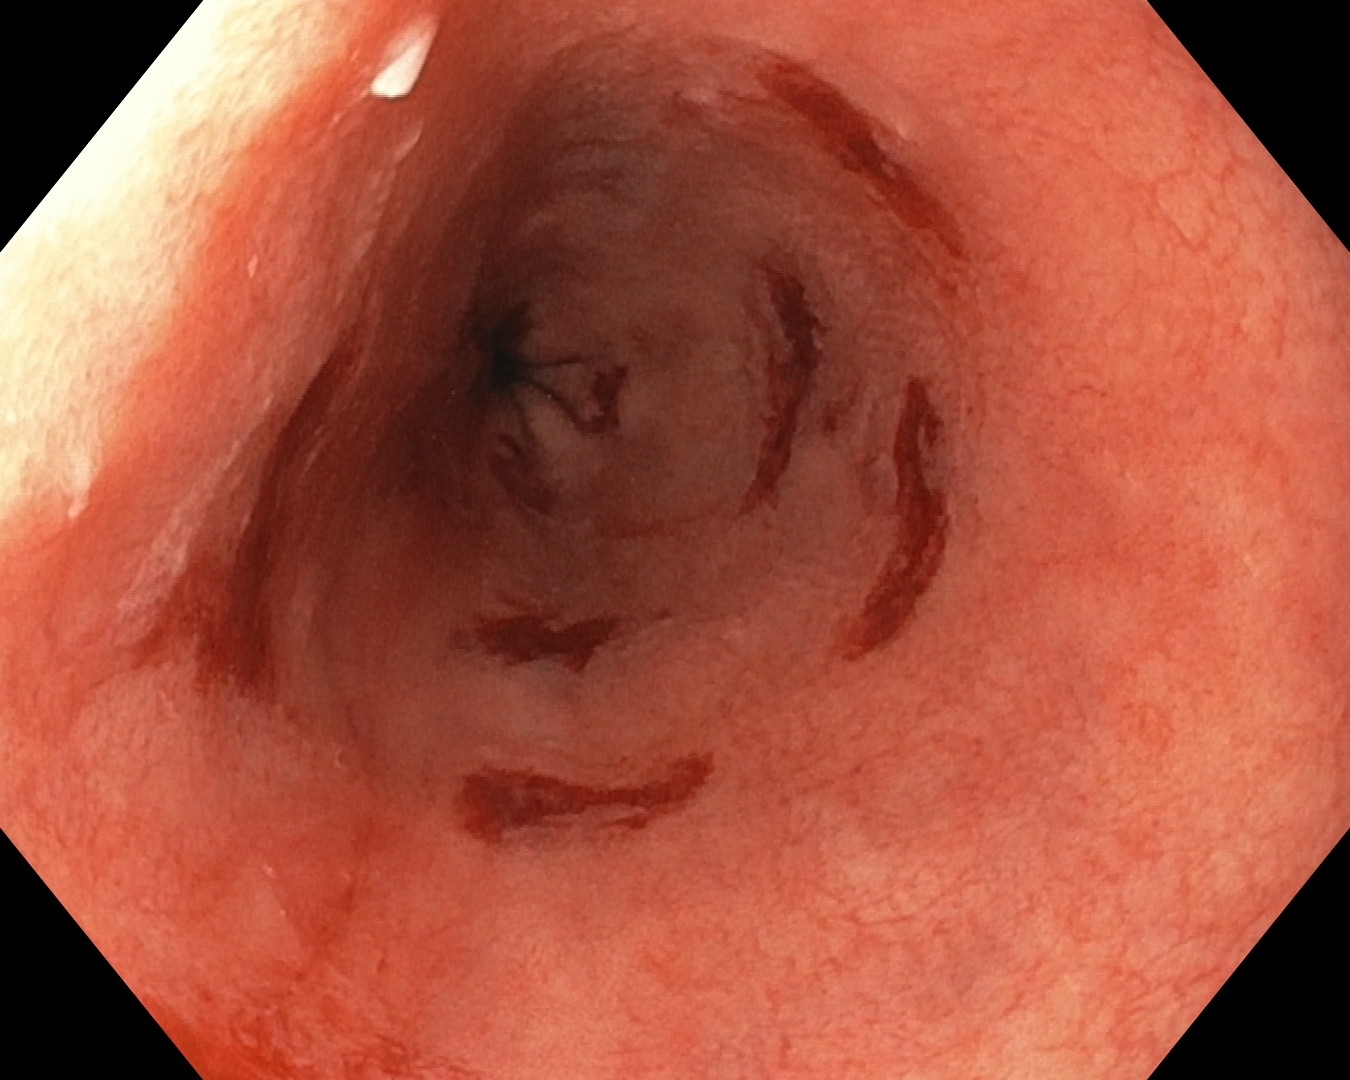
Experienced teaching points
Clinical Pearls
- Do not biopsy an irregular Z-line under 1 cm and call it Barrett. ACG 2022 requires at least 1 cm of salmon mucosa plus intestinal metaplasia.
- Report Prague C (circumferential) and M (maximal tongue) from the top of the gastric folds. M is never shorter than C. Photograph islands separately.
- HD white light plus chromoendoscopy (acetic acid or virtual), then target every visible lesion, then Seattle four-quadrant biopsies. Chromo does not replace Seattle.
- Confirmed high-grade dysplasia or T1a: resect the visible lesion first, then ablate remaining flat Barrett. Do not burn over a lump.
- Confirmed low-grade dysplasia: endoscopic eradication is reasonable. If you survey instead, do it on a tight interval after expert pathology, not on a 3- to 5-year NDBE clock.
Clinical Bottom Line
| Question | 2026 practical answer |
|---|---|
| What counts as Barrett? | Salmon-colored mucosa extending at least 1 cm above the top of the gastric folds, plus intestinal metaplasia on histology. ACG 2022. Report it with Prague C&M. |
| What is not Barrett? | An irregular Z-line or tongues under 1 cm. Do not biopsy that mucosa as Barrett and do not enroll it in surveillance. Reliability of Prague under 1 cm is poor, and progression risk is near zero. |
| Prague C&M | C is circumferential extent in cm. M is the maximal tongue. Both are measured from the GEJ (top of the gastric folds). M is never less than C. Record islands separately. |
| Inspection | High-definition white light plus chromoendoscopy (dilute acetic acid or virtual: NBI, BLI, i-SCAN). ESGE: at least 1 minute per cm of Barrett length, photographs, retroflexed cardia. |
| Biopsy | Target every visible lesion (Paris class, own jar), then Seattle four-quadrant biopsies every 2 cm (every 1 cm if known dysplasia). Chromo-targeted biopsies do not replace Seattle. |
| NDBE interval | Maximum extent under 3 cm: 5 years. At least 3 cm: 3 years (ACG 2022, strong). ESGE sends maximum extent of at least 10 cm to an expert center. Stop when the patient is no longer an eradication candidate. |
| Indefinite for dysplasia | Expert GI pathologist first. Twice-daily PPI. Repeat EGD within 6 months with a high-quality Seattle exam. Persistent IND: yearly until it resolves or upgrades. |
| Visible lesion | Resect first (band EMR; ESD if you need en bloc for a large or possibly invasive lesion). Do not ablate over a lump. |
| HGD or T1a | Endoscopic eradication over esophagectomy for most patients (ACG strong). Ablate remaining flat Barrett after resection to reach complete eradication of intestinal metaplasia (CEIM). |
| Confirmed LGD | ACG: eradication is recommended; surveillance at 6 months, 12 months, then yearly is acceptable. ESGE: ablate after LGD on two separate endoscopies, both expert-confirmed. |
| After CEIM | ACG: LGD at 1 year, 3 years, then every 2 years. HGD or intramucosal cancer at 3, 6, and 12 months, then yearly. Inspect neo-SCJ and cardia. Do not stop because the squamous looks clean. |
What counts as Barrett esophagus?
The diagnosis is endoscopic plus histologic. ACG 2022 wants salmon-colored columnar mucosa in the tubular esophagus that extends at least 1 cm proximal to the top of the gastric folds, with intestinal metaplasia on biopsy. Anything shorter is an irregular Z-line. Do not label it Barrett. Do not put it on a 3- or 5-year clock.

That 1 cm threshold is not pedantry. Prague C&M reliability collapses under 1 cm (coefficient 0.22 in the original validation). Olmsted County follow-up found no HGD or cancer in intestinal metaplasia confined to the GEJ, against a real progression rate once the segment is at least 1 cm. About half of irregular Z-lines never show intestinal metaplasia again. The cost of a false Barrett label is lifelong surveillance, insurance loading, and a patient who thinks they have a premalignant esophagus.
Screening who to scope is a different question (chronic GERD in men with extra risk factors). This page is the exam and the pathway after you already see salmon mucosa. Gastric intestinal metaplasia is a different map. Do not run Barrett intervals on the stomach. That lives on the gastric cancer prevention page.
How do I report Prague C&M?
Sharma's 2006 Prague criteria remain the shared language. Identify the GEJ as the proximal margin of the gastric folds, with the esophagus decompressed enough that the folds are not flattened out of existence. Record:
- C: circumferential extent of continuous salmon mucosa, in cm above the GEJ.
- M: maximal extent, including the longest tongue.
- Islands of columnar mucosa that are not continuous with the main segment. They do not change C or M. Write them in the report and photograph them. After ablation they are often the residue that still needs treatment.
- Diaphragmatic hiatus if a hernia is present, so the next endoscopist can find the same GEJ.
M is always at least C. A C0M2 is a pair of tongues without a circumferential collar. A C3M5 is a 3 cm collar plus a 2 cm extra tongue. "Short-segment" and "long-segment" are still useful shorthand (<3 cm vs at least 3 cm) because that is how ACG now splits NDBE intervals, but Prague is what you write in the note.
Trainees can learn this. Vahabzadeh showed high C and M agreement among fellows once landmarks are taught. Photograph the segment in overview, then close-up, then retroflexed cardia. ESGE 2023 wants one picture per cm of Barrett length. That is how you prove the next exam is looking at the same mucosa.
How should I inspect and biopsy?
ACG 2022 makes HD white light plus chromoendoscopy a strong recommendation for surveillance. Chromoendoscopy here means dilute acetic acid (about 1.5% to 2.5%) or virtual chromoendoscopy. Acetic acid whitens Barrett mucosa; dysplastic areas lose that whitening faster (pooled sensitivity 0.92 and specificity 0.96 for HGD/EAC in the meta-analysis ACG cites). Virtual chromo (NBI and cousins) scores mucosa and vessels as regular or irregular. Sharma's NBI-versus-Seattle crossover found more dysplasia with NBI-targeted biopsies, and every dysplastic area had an irregular pattern.
That does not give you permission to skip Seattle. ACG is explicit: chromo-directed biopsies are an add-on. Worldwide Seattle adherence is about 50%, and it falls as the segment gets longer, which is exactly when sampling error hurts. Nonadherence cuts dysplasia detection roughly in half. The sequence on a surveillance list:
- Wash. Deflate enough to see the folds. Find the GEJ and the hiatus.
- Spend time. ESGE: at least 1 minute of inspection per cm of Barrett length. Longer inspection finds more HGD and cancer.
- HD white light in overview, then chromoendoscopy close-up. Photograph landmarks, the segment, any lesion, and the cardia in retroflex.
- Resect or biopsy every visible lesion into its own jar. Use Paris. A slightly raised or depressed patch is not a random quadrant.
- Then Seattle: four quadrants every 2 cm. Drop to every 1 cm if the indication is known dysplasia. ACG also suggests at least 8 biopsies when the segment is short; follow Seattle once length is over 4 cm.
- A partially deflated esophagus makes the quadrants reachable. Do not biopsy through a lake of blood or food.
WATS-3D and TissueCypher did not earn an ACG recommendation. They are adjuncts at best. They do not replace a slow look and a complete Seattle set.
What is the dysplasia pathway?
Pathology agreement is good for NDBE and HGD and poor for indefinite and low-grade dysplasia. A community LGD diagnosis is often not LGD. In the Dutch review that ACG leans on, expert pathologists downstaged 73% of community LGD; confirmed LGD then progressed at 9.1% per patient-year, against 0.6% when it was really NDBE. Always send dysplasia (and IND) to an expert GI pathologist before you change the plan.
Indefinite for dysplasia. Confirm the read. Maximize acid suppression (twice-daily PPI if not already there). Repeat a high-quality exam within 6 months. If it is NDBE, go to the length-based clock. If IND persists, ACG surveys yearly until it resolves or upgrades. Do not ablate IND.
NDBE. ACG 2022 (strong): maximum extent under 3 cm, every 5 years; at least 3 cm, every 3 years. That assumes the index exam was high quality with Seattle sampling. ESGE 2023 uses the same 5-year / 3-year split and sends maximum extent of at least 10 cm to an expert Barrett center. Consider stopping when the patient would no longer undergo eradication, often around age 75 or when life expectancy is under 5 years (ESGE). ACG's quality language is the same idea: do not survey someone who cannot be treated.
Most postendoscopy esophageal cancers are missed lesions, not biology that appeared in 90 days. If the last exam was a 4-minute look without chromo and without Seattle, the next exam is a catch-up, not a 5-year slot.
When do I eradicate versus watch?
The treatment order is the same in ACG 2022 and ESGE 2023: find and resect visible neoplasia, then ablate remaining flat Barrett until CEIM. Radiofrequency ablation has the RCT record (AIM Dysplasia; SURF for LGD). Cryotherapy is a salvage or alternative ablative tool, not the first default when RFA is available.
Confirmed HGD or intramucosal (T1a) cancer. EET over esophagectomy is a strong ACG recommendation for most patients. Lymph-node risk is near 0% in HGD and about 2% in T1a. Cap or band EMR handles most visible lesions. ESD is for lesions that need en bloc resection because of size or suspected submucosal invasion, or for fibrotic recurrence after ablation. After the lump is out, ablate the rest of the segment. Leaving residual Barrett after a focal EMR is how you get a metachronous cancer.
T1b. That is no longer a routine endoscopy-only disease. ESGE allows endoscopic resection for low-risk submucosal disease (invasion ≤500 µm, no lymphovascular invasion, not poorly differentiated) in an expert center with EUS and cross-sectional follow-up. Deep submucosal invasion, LVI, or poor differentiation needs multidisciplinary staging. Do not promise CEIM as a cancer operation in that group.
Confirmed LGD. ACG recommends EET and still allows surveillance (6 months, 12 months, then yearly) after shared decision. ESGE is firmer: offer ablation when LGD is confirmed on at least two separate endoscopies by a second experienced pathologist. SURF is why. If you watch LGD, you are not on an NDBE interval.
After CEIM. Recurrence of intestinal metaplasia is about 9% to 10% per year in meta-analysis; dysplastic recurrence is lower but not zero. ACG intervals follow pretreatment histology: LGD at 1 year, 3 years, then every 2 years; HGD or intramucosal cancer at 3, 6, and 12 months, then yearly. Inspect neo-squamous epithelium and the cardia in anteflex and retroflex with HD white light and virtual chromo. Biopsy the GEJ and the distal 2 to 5 cm of esophagus even when it looks squamous; ACG still wants those samples. ESGE 2023 drops routine four-quadrant neo-squamous biopsies and keeps GEJ samples plus targeted biopsies of anything that looks like recurrent Barrett. Use ACG sampling in U.S. practice unless your center has an explicit ESGE protocol. ESGE also time-limits post-EET surveillance (HGD/EAC through year 10, LGD through year 5). ACG does not stop. Do not discharge a CEIM patient because the mucosa "looks healed."
Centers that do this work should track complete eradication of dysplasia, CEIM, stricture, and buried Barrett. That is an ACG quality expectation, not a marketing metric.
Selected references
- Shaheen NJ, Falk GW, Iyer PG, et al. Diagnosis and Management of Barrett's Esophagus: An Updated ACG Guideline. Am J Gastroenterol. 2022;117:559-587.
- Sharma P, Dent J, Armstrong D, et al. The development and validation of an endoscopic grading system for Barrett's esophagus: the Prague C & M criteria. Gastroenterology. 2006;131:1392-1399.
- Weusten BLAM, Bisschops R, Dinis-Ribeiro M, et al. Diagnosis and management of Barrett esophagus: ESGE Guideline. Endoscopy. 2023;55:1124-1146.
- Shaheen NJ, Sharma P, Overholt BF, et al. Radiofrequency ablation in Barrett's esophagus with dysplasia. N Engl J Med. 2009;360:2277-2288.
- Phoa KN, van Vilsteren FGI, Weusten BLAM, et al. Radiofrequency ablation vs endoscopic surveillance for patients with Barrett esophagus and low-grade dysplasia: the SURF trial. JAMA. 2014;311:1209-1217.
- Wani S, Qumseya B, Sultan S, et al. ASGE guideline: endoscopic eradication therapy for patients with Barrett's esophagus-associated dysplasia and intramucosal cancer. Gastrointest Endosc. 2018;87:907-931.e9.
- Sharma P, Hawes RH, Bansal A, et al. Standard endoscopy with random biopsies vs narrow band imaging targeted biopsies in Barrett's oesophagus. Gut. 2013;62:15-21.
- Gupta N, Gaddam S, Wani SB, Bansal A, Rastogi A, Sharma P. Longer inspection time is associated with increased detection of high-grade dysplasia and esophageal adenocarcinoma in Barrett's esophagus. Gastrointest Endosc. 2012;76:531-538.
Last reviewed September 20, 2026. Written for clinicians surveying Barrett esophagus and deciding when endoscopic eradication is the next step, not a stomach-cancer screening page.
For your teaching file
Save this article as a PDF
Drop your email and we'll open a print-ready version you can save as a PDF — and you'll start getting our weekly GI endoscopy newsletter.